
First published: Mar 21, 2023
Last updated: September 27, 2026
Written and source- checked by: Adel Galal, Founder and Lead Writer at NextFitLife
Medical review status: Educational health content. This article has not been medically reviewed by a hepatologist, infectious disease specialist, doctor, pharmacist, or registered dietitian.
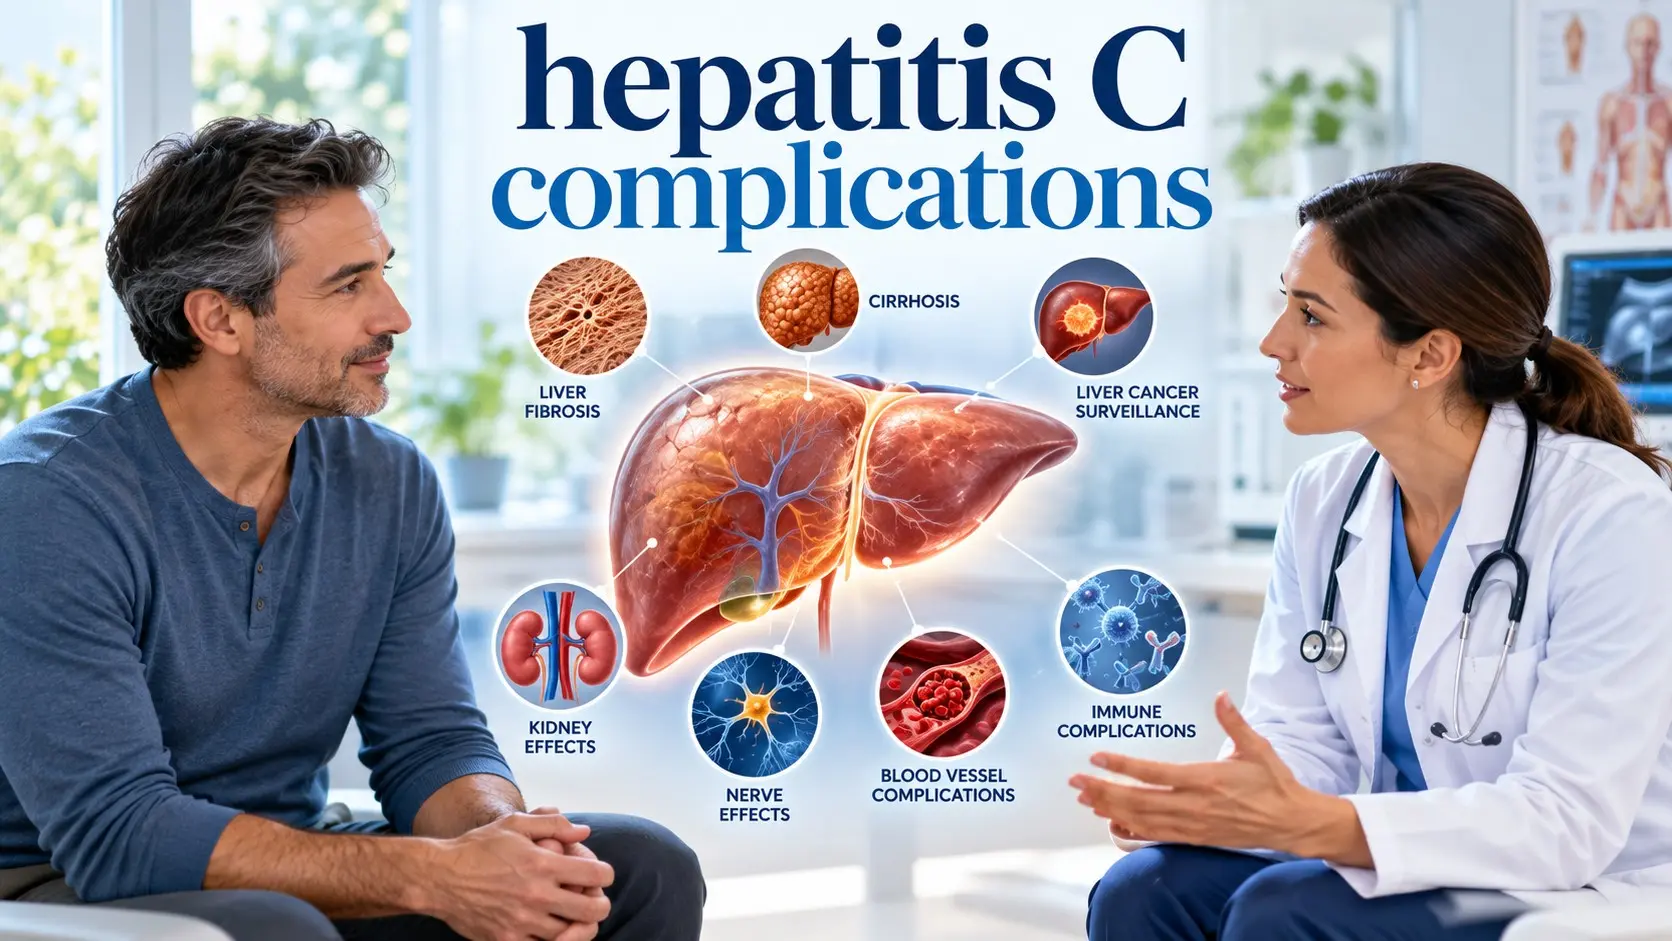
Hepatitis C can quietly damage the liver for years before a person feels sick. It can also affect the kidneys, blood vessels, nerves, skin, immune system, and other parts of the body.
The good news is very different from what it was years ago.
Modern direct acting antiviral treatment cures more than 95% of hepatitis C infections. Treating the virus early can prevent cirrhosis, liver failure, liver cancer, and many problems outside the liver.
Quick answer: The most serious hepatitis C complications include liver fibrosis, cirrhosis, portal hypertension, internal bleeding, ascites, hepatic encephalopathy, liver failure, and liver cancer. Chronic HCV can also be linked with cryoglobulinemic vasculitis, kidney disease, nerve problems, skin conditions, lymphoma, diabetes, and other conditions. Cure lowers many risks, but people who already have cirrhosis still need long term liver cancer surveillance.
That last point is easy to miss.
Curing hepatitis C does not always mean liver follow up ends. If cirrhosis was already present before treatment, the risk of hepatocellular carcinoma falls after cure but does not disappear.
Medical notice: I am not a dermatologist or a doctor, and this content does not replace professional medical advice. What I share comes from real life experience, extensive research, and consultation with healthcare providers. Always consult qualified medical professionals for diagnosis and treatment of any health condition.
Table of Contents
- What hepatitis C complications mean
- 17 critical complications and related conditions
- Fibrosis versus cirrhosis
- Portal hypertension and internal bleeding
- Ascites and hepatic encephalopathy
- Liver cancer risk
- Kidney, nerve, skin, and immune problems
- What treatment changes
- What happens after hepatitis C cure
- Who still needs liver cancer screening
- How doctors check liver damage
- Factors that increase complication risk
- Food, alcohol, medicine, and supplement safety
- Emergency warning signs
- References and Sources
- Related NextFitLife guides
- About the author
- Frequently asked questions
What Are Hepatitis C Complications?
Hepatitis C is caused by the hepatitis C virus, usually called HCV.
HCV is mainly a bloodborne infection. After infection, some people clear the virus without treatment, but more than half develop chronic infection.
Chronic HCV can keep causing low level liver inflammation for years.
This can create scar tissue called fibrosis. As more scar tissue forms, fibrosis can advance to cirrhosis.
Cirrhosis changes the structure of the liver and can block normal blood flow through it. That is where many of the most serious complications begin.
HCV can also trigger immune and inflammatory problems outside the liver. These are called extrahepatic manifestations.
For a wider guide to hepatitis A, B, C, D, and E, read the NextFitLife Hepatitis Causes, Symptoms, Treatment, and Prevention Guide.
17 Critical Hepatitis C Complications and Related Conditions
1. Liver Fibrosis
Liver fibrosis means scar tissue is forming in the liver.
It develops when repeated inflammation and liver cell injury cause the body to lay down collagen and other scar material.
Early fibrosis may cause no symptoms.
This is why feeling well does not prove the liver is healthy.
Fibrosis can sometimes improve after hepatitis C is cured, especially before it has reached advanced cirrhosis.
2. Cirrhosis
Cirrhosis is advanced liver scarring.
Healthy liver structure is replaced by scar tissue and regenerative nodules. Blood has more difficulty flowing through the organ, and liver function can fall.
CDC estimates that about 5% to 25% of people with chronic hepatitis C develop cirrhosis over 10 to 20 years.
The risk varies widely. Treatment before advanced fibrosis develops can greatly change the outlook.
3. Portal Hypertension
The portal vein carries blood from the digestive organs to the liver.
When cirrhosis blocks normal flow, pressure can rise in this system. This is called portal hypertension.
Portal hypertension can lead to:
- An enlarged spleen
- Low platelet counts
- Swollen veins in the esophagus or stomach
- Ascites
- Other signs of decompensated liver disease
The virus itself does not suddenly create high portal pressure. The problem usually develops because advanced liver scarring changes blood flow.
4. Esophageal or Gastric Varices
Portal hypertension can force blood into smaller veins around the esophagus and stomach.
These enlarged veins are called varices.
They can rupture and bleed heavily.
Vomiting blood or passing black, tar like stool is an emergency.
People with cirrhosis may need evaluation and monitoring for varices based on current liver disease guidance.
5. Ascites
Ascites is fluid buildup in the abdomen.
It is usually a complication of advanced cirrhosis and portal hypertension, not a typical short term complication of uncomplicated acute hepatitis C.
The abdomen can become swollen or uncomfortable. Large amounts of fluid can also make breathing or eating difficult.
Treatment can involve sodium management, medicines called diuretics, drainage procedures, and specialist liver care.
6. Hepatic Encephalopathy
Hepatic encephalopathy affects brain function when a damaged liver can no longer handle substances in the blood normally.
Symptoms can include:
- Confusion
- Poor concentration
- Sleep pattern changes
- Personality changes
- Slurred speech
- Severe sleepiness
New confusion in someone with cirrhosis needs urgent medical assessment.
Hepatic encephalopathy is a complication of severe liver dysfunction, not simply the presence of HCV in the bloodstream.
7. Enlarged Spleen and Low Platelets
Portal hypertension can cause the spleen to enlarge.
The enlarged spleen may hold more platelets than normal, contributing to thrombocytopenia, which means a low platelet count.
Advanced liver disease can also reduce production of proteins needed for normal blood clotting.
This helps explain why easy bruising or abnormal bleeding can appear in advanced disease.
A low platelet count alone does not prove that someone has cirrhosis, but it can be an important clue.
8. Liver Failure
As cirrhosis becomes more severe, the liver can lose its ability to perform essential jobs.
This is called liver failure or end stage liver disease.
Signs can include:
- Jaundice
- Ascites
- Bleeding
- Confusion
- Severe weakness
- Muscle loss
- Kidney problems
Some people with advanced liver failure need evaluation for liver transplantation.
9. Hepatocellular Carcinoma
Hepatocellular carcinoma, or HCC, is the main form of primary liver cancer.
Chronic HCV increases HCC risk mainly through long term liver injury and cirrhosis.
CDC states that people with hepatitis C related cirrhosis have an annual HCC risk of roughly 1% to 4%.
Curing the virus lowers that risk.
It does not reduce the risk to zero once cirrhosis has developed.
After cure: AASLD and IDSA guidance still recommends liver cancer surveillance for people with cirrhosis, usually with liver ultrasound every 6 months, with or without alpha fetoprotein testing according to the surveillance plan.
10. Mixed Cryoglobulinemia and Vasculitis
HCV can trigger production of abnormal immune proteins called cryoglobulins.
These proteins can clump when blood gets cooler and form immune complexes that inflame small and medium blood vessels.
This condition is called cryoglobulinemic vasculitis.
Symptoms can include:
- Purple spots on the legs called purpura
- Joint pain
- Fatigue
- Weakness
- Nerve pain
- Kidney disease
Not every person who has cryoglobulins in a blood test has symptomatic vasculitis.
Current HCV guidance treats symptomatic cryoglobulinemia as an important reason to start antiviral treatment promptly.
11. Kidney Disease
Chronic hepatitis C is linked with several kidney problems.
The best known is membranoproliferative glomerulonephritis, often connected with cryoglobulinemic vasculitis.
Possible signs include:
- Protein in the urine
- Blood in the urine
- High blood pressure
- Swelling
- Reduced kidney function
Current HCV guidance notes that chronic HCV is independently associated with chronic kidney disease and that successful antiviral treatment can improve kidney outcomes in selected patients.
12. Peripheral Neuropathy
Some people with HCV related cryoglobulinemia develop peripheral neuropathy.
This means nerves outside the brain and spinal cord become damaged or inflamed.
Symptoms can include:
- Burning pain
- Tingling
- Numbness
- Electric shock sensations
- Weakness
Diabetes and many other conditions can also cause neuropathy, so nerve symptoms need proper assessment rather than being automatically blamed on HCV.
13. Porphyria Cutanea Tarda
Porphyria cutanea tarda, or PCT, is a skin condition associated with abnormal porphyrin processing.
Hepatitis C is one recognized risk factor.
Symptoms can include:
- Fragile skin
- Blisters on sun exposed areas
- Slow healing
- Changes in skin color
HCV treatment may be part of the plan when active infection is present, but PCT itself can need separate care.
14. Lichen Planus
Lichen planus is an inflammatory condition that can affect the skin or mouth.
Research has found an association between HCV and lichen planus, although the strength of the relationship differs between regions and studies.
This is a better description than claiming that HCV is the cause of every case.
Persistent mouth sores, painful oral changes, or a new unexplained skin rash should be assessed professionally.
15. B Cell Non Hodgkin Lymphoma
Chronic immune stimulation from HCV has been linked with certain B cell lymphomas.
These cancers affect cells of the immune system.
The risk for an individual remains much lower than the risk of common HCV liver complications, but the connection is strong enough to matter clinically.
AASLD and IDSA guidance notes that some HCV associated lymphoproliferative disorders can improve or enter remission after successful antiviral therapy.
That is another reason treatment should not be delayed simply because liver enzymes look acceptable.
16. Insulin Resistance and Type 2 Diabetes
Chronic HCV has been associated with insulin resistance and type 2 diabetes.
The relationship is complex.
Age, body weight, family history, liver disease severity, activity, diet, and other metabolic factors also affect diabetes risk.
It is therefore more accurate to describe diabetes as an important HCV associated condition rather than saying the virus alone causes every case.
For the wider link between diabetes and organ health, see the NextFitLife Diabetes and Heart Diseases Guide.
17. Cardiovascular Disease Association
Research also links chronic HCV with a higher rate of some cardiovascular events.
The exact relationship is still being studied.
HCV related inflammation, metabolic changes, diabetes, kidney disease, smoking, age, blood pressure, and other risk factors can overlap.
For this reason, I would not describe heart disease as a guaranteed direct complication of hepatitis C.
It is better viewed as an important association that adds to the reason for treating HCV and controlling ordinary cardiovascular risk factors.
Liver Complications Versus Extrahepatic Complications
The easiest way to understand the list is to divide it into two groups.
| Group | Examples | Main Driver |
|---|---|---|
| Liver related complications | Fibrosis, cirrhosis, portal hypertension, varices, ascites, encephalopathy, liver failure, HCC | Progressive liver inflammation, fibrosis, and cirrhosis |
| Extrahepatic manifestations | Cryoglobulinemia, kidney disease, neuropathy, PCT, lichen planus, some lymphomas, metabolic and cardiovascular associations | Immune effects, inflammation, metabolic effects, or other HCV related mechanisms |
This distinction matters because someone can have an HCV related problem outside the liver even without obvious symptoms of cirrhosis.
What Is the Difference Between Fibrosis and Cirrhosis?
Fibrosis is liver scarring.
Cirrhosis is advanced scarring that changes the liver's structure and blood flow.
You can think of the process as a spectrum:
Inflammation → Fibrosis → Advanced Fibrosis → Cirrhosis → Possible Decompensation
The important word is possible.
Progression is not automatic, and modern HCV treatment can stop the virus before many people reach advanced disease.
What Is Compensated Versus Decompensated Cirrhosis?
Compensated cirrhosis means the liver is badly scarred but still performs enough of its basic functions that major cirrhosis complications have not appeared.
A person can feel fairly well at this stage.
Decompensated cirrhosis means serious complications have developed.
Examples include:
- Ascites
- Variceal bleeding
- Hepatic encephalopathy
- Severe jaundice
Decompensated cirrhosis needs specialist liver care.
Why Early Treatment Changes the Risk
The goal of modern hepatitis C treatment is a sustained virologic response, often shortened to SVR.
This means HCV RNA remains undetectable after treatment at the required follow up point.
SVR is considered a virologic cure.
Current HCV guidance recommends treatment for almost everyone with acute or chronic hepatitis C because cure reduces:
- Ongoing liver inflammation
- Fibrosis progression
- Liver failure risk
- Liver related death
- Hepatocellular carcinoma risk
- Transmission of HCV
- Several extrahepatic complications
Cure can also allow some liver fibrosis to regress.
The earlier HCV is treated, the more damage can potentially be prevented.
How Effective Is Modern Hepatitis C Treatment?
Very effective.
Current CDC, WHO, and AASLD guidance states that oral direct acting antivirals cure more than 95% of treated HCV infections.
Many treatment courses last about 8 to 12 weeks.
The exact medicine depends on factors such as:
- Whether cirrhosis is present
- Whether the liver is compensated or decompensated
- Previous HCV treatment
- Other medicines
- Kidney function
- Pregnancy considerations
- Other infections such as hepatitis B or HIV
Do not choose an antiviral regimen from an online article.
How Do You Know if Hepatitis C Is Cured?
A positive antibody test is not enough.
HCV antibodies can stay positive after the virus has been cured.
To confirm cure, clinicians use an HCV RNA test.
AASLD and IDSA guidance recommends quantitative HCV RNA testing 12 weeks or more after treatment to confirm sustained virologic response.
If HCV RNA is undetectable at that point, the infection is considered cured.
Does Cure End All Follow Up?
It depends on whether cirrhosis was already present.
| After HCV Cure | Typical Follow Up |
|---|---|
| No cirrhosis | Routine liver related follow up is generally the same as for someone who was never infected, unless another liver problem is present |
| Cirrhosis present | Continue HCC surveillance and cirrhosis care even after HCV cure |
| Ongoing HCV exposure risk | Periodic HCV RNA testing because reinfection can occur |
This is one of the most important distinctions in modern HCV care.
Why Does Liver Cancer Screening Continue After Cure?
Cure stops the virus.
It does not instantly erase advanced scar tissue.
A liver that already has cirrhosis still carries a higher HCC risk than a liver that never developed cirrhosis.
Current AASLD and IDSA guidance therefore recommends ongoing hepatocellular carcinoma surveillance for people with cirrhosis after SVR.
The usual surveillance interval is every 6 months using liver ultrasound, with or without alpha fetoprotein according to the clinical plan.
Do not stop this surveillance simply because HCV RNA becomes undetectable.
Can Hepatitis C Come Back After Cure?
A true sustained virologic response is highly durable.
But cure does not create immunity.
You can get a new HCV infection after another exposure.
This is called reinfection.
People with ongoing exposure risk should receive prevention support and periodic HCV RNA testing.
Using an antibody test to look for reinfection is not useful because the antibody may stay positive from the old infection.
What Increases the Risk of Hepatitis C Complications?
Not every person with chronic HCV progresses at the same speed.
Risk can be affected by:
- How long the infection has been present
- Older age
- Advanced fibrosis at diagnosis
- Heavy alcohol use
- HIV coinfection
- Hepatitis B coinfection
- Metabolic liver disease
- Diabetes
- Obesity
- Smoking
- Delayed HCV treatment
The old idea that a higher HCV viral load automatically predicts worse liver scarring is too simple.
Viral load is useful for diagnosis and treatment monitoring, but it does not directly tell you how much fibrosis a person has.
How Do Doctors Check for Liver Damage?
HCV RNA tells doctors whether the virus is present.
It does not measure liver scarring.
Doctors may use:
- ALT and AST
- Platelet count
- Bilirubin
- Albumin
- INR
- FIB 4
- APRI
- Ultrasound
- Transient elastography
- Other imaging
- Occasionally liver biopsy
Current HCV guidance states that staging liver fibrosis before treatment is essential because the presence of cirrhosis changes treatment and long term follow up.
What About Fatty Liver After Hepatitis C Cure?
HCV cure does not protect the liver from every other liver disease.
A person can still have metabolic dysfunction associated steatotic liver disease, alcohol related liver disease, medicine related injury, hepatitis B, autoimmune liver disease, or another cause of abnormal liver tests.
If liver enzymes remain abnormal after HCV cure, current guidance recommends looking for other liver disease causes.
For more on metabolic liver disease, read the NextFitLife Fatty Liver Disease Treatment Guide.
Should You Drink Alcohol With Hepatitis C?
Alcohol adds another source of liver injury.
People with chronic HCV or HCV related cirrhosis should discuss alcohol use with their liver team.
Current HCV guidance advises people with cirrhosis to abstain from alcohol.
If you drink heavily every day and may be physically dependent, do not suddenly stop without medical help because severe alcohol withdrawal can be dangerous.
What Should You Eat With Hepatitis C?
There is no special food that clears HCV from the blood.
Direct acting antiviral medicine cures the infection.
A balanced eating pattern can still support liver and general health.
Foods may include:
- Vegetables
- Whole fruit
- Whole grains
- Beans and lentils when tolerated
- Fish
- Eggs
- Poultry
- Tofu
- Plain yogurt when suitable
- Nuts
- Seeds
- Unsaturated fats
Cirrhosis, ascites, kidney disease, diabetes, poor appetite, muscle loss, or malnutrition can change nutrition needs.
Those situations need individual advice.
Use the NextFitLife Nutrition and Vitamins Hub for broader food and supplement guidance.
Can Liver Detox Supplements Prevent Complications?
No detox product has been proven to cure hepatitis C.
Milk thistle, detox teas, herbal powders, high dose vitamins, juice cleanses, and other supplements cannot replace antiviral treatment.
Some supplements can damage the liver or interact with medicine.
Tell your healthcare professional about every supplement you use before starting HCV treatment.
When Is Hepatitis C an Emergency?
Seek urgent medical care if someone with hepatitis C or cirrhosis develops:
- Vomiting blood
- Black tar like stool
- New confusion
- Extreme sleepiness
- Fainting
- Severe jaundice
- Rapidly increasing abdominal swelling
- Severe shortness of breath
- Severe weakness
- Repeated vomiting
- Unusual bleeding
- A major sudden change in mental state
These symptoms can occur with serious complications such as variceal bleeding, encephalopathy, infection, or advanced liver failure.
What I Would Correct From Older Hepatitis C Advice
Several older statements deserve updating.
- Ascites is not a usual short term complication of simple acute HCV. It is much more commonly linked with advanced cirrhosis and portal hypertension.
- Hepatic encephalopathy is not ordinary early HCV brain damage. It usually occurs when advanced liver dysfunction prevents normal toxin handling.
- HCV treatment does more than suppress the virus. Modern direct acting antivirals cure more than 95% of infections.
- Viral load is not a fibrosis score. A high RNA level does not by itself tell you how badly the liver is scarred.
- Not every extrahepatic condition has equally strong evidence. Cryoglobulinemia, kidney disease, and some B cell lymphomas have stronger HCV links than several other reported associations.
- Cure does not always end surveillance. Cirrhosis still requires ongoing HCC screening after SVR.
Conclusion
The most serious hepatitis C complications develop when chronic infection causes years of liver injury or triggers disease outside the liver. Fibrosis, cirrhosis, portal hypertension, liver failure, liver cancer, cryoglobulinemia, kidney disease, nerve problems, and several immune related conditions can all occur.
The most useful next step is not waiting for symptoms. If you have active HCV, ask about direct acting antiviral treatment. If you have already been cured, find out whether you ever developed cirrhosis. That one answer determines whether routine follow up may be enough or whether liver cancer surveillance must continue every 6 months.
References and Sources
The complication, treatment, cure, and follow up information in this article was checked against current government, liver society, and university based hepatitis guidance. Full URLs are provided for verification.
- Centers for Disease Control and Prevention.
Clinical Overview of Hepatitis C.
Used for current HCV transmission, treatment success, cirrhosis risk, HCC risk, extrahepatic complications, and prevention information.
URL:
https://www.cdc.gov/hepatitis-c/hcp/clinical-overview/index.html
- World Health Organization.
Hepatitis C Fact Sheet.
Updated July 28, 2026.
Used for current worldwide HCV data, complications, transmission, and the greater than 95% cure rate with direct acting antiviral treatment.
URL:
https://www.who.int/news-room/fact-sheets/detail/hepatitis-c
- AASLD and IDSA HCV Guidance.
Recommendations for Testing, Managing, and Treating Hepatitis C.
Updated in 2026.
Used for treatment recommendations, fibrosis staging, cure, post treatment follow up, liver cancer surveillance, reinfection testing, and extrahepatic HCV conditions.
URL:
https://www.hcvguidelines.org/
- National Institute of Diabetes and Digestive and Kidney Diseases.
Hepatitis C.
Used for chronic HCV complications including cirrhosis, liver failure, liver cancer, treatment, diagnosis, and liver monitoring.
URL:
https://www.niddk.nih.gov/health-information/liver-disease/viral-hepatitis/hepatitis-c
- University of Washington Hepatitis C Online.
Extrahepatic Conditions Related to HCV Infection.
Used for current information on cryoglobulinemia, kidney disease, skin manifestations, diabetes, lymphoma, neuropathy, and cardiovascular associations.
URL:
https://www.hepatitisc.uw.edu/go/evaluation-staging-monitoring/extrahepatic-conditions/core-concept/all
- AASLD and IDSA HCV Guidance.
Monitoring Persons Who Are Starting HCV Treatment, Are on Treatment, or Have Completed Antiviral Therapy.
Used for SVR confirmation, post cure care, HCC surveillance, variceal monitoring, HCV recurrence testing, and management after treatment failure.
URL:
https://www.hcvguidelines.org/guidance/monitoring-patients-who-are-starting-hcv-treatment-are-on-treatment-or-have-completed-therapy/
Continue With NextFitLife Liver and Health Guides
Use these related guides to understand hepatitis, liver scarring, metabolic liver disease, nutrition, and related health risks.
Hepatitis and Liver Health
Metabolic and General Health
About the Author
Adel Galal is the founder and lead writer of NextFitLife. He has more than 15 years of health and wellness writing and research communication experience, with more than 30 years of personal interest in health, nutrition, fitness, sleep, wellness, and healthy aging.
His work focuses on comparing medical and public health guidance, identifying claims that are outdated or stronger than the available evidence, and explaining health information in clear language for everyday readers.
For hepatitis and liver health topics, the goal is to distinguish infection from liver damage, separate direct liver complications from conditions outside the liver, and make clear when cure changes follow up and when ongoing surveillance is still needed.
I am not a dermatologist or a doctor, and this content does not replace professional medical advice. What I share comes from real life experience, extensive research, and consultation with healthcare providers. Always consult qualified medical professionals for diagnosis and treatment of any health condition.
Learn more about Adel Galal, NextFitLife, the site's research process, and editorial standards on the NextFitLife About Us page.
Frequently Asked Questions About Hepatitis C Complications
What are the main complications of hepatitis C?
The major liver complications include fibrosis, cirrhosis, portal hypertension, varices, ascites, hepatic encephalopathy, liver failure, and hepatocellular carcinoma. HCV can also be linked with cryoglobulinemia, kidney disease, nerve problems, skin conditions, lymphoma, and several metabolic conditions.
How long does hepatitis C take to damage the liver?
Progression varies widely. CDC estimates that about 5% to 25% of people with chronic hepatitis C develop cirrhosis over 10 to 20 years. Some people progress faster, while others may never develop cirrhosis.
Can hepatitis C be cured?
Yes. Modern direct acting antiviral medicines cure more than 95% of hepatitis C infections. Cure is confirmed with an HCV RNA test after treatment.
Can liver damage improve after hepatitis C is cured?
Yes. Liver inflammation usually falls after cure, and fibrosis can improve in many people. Advanced cirrhosis may not fully disappear, so long term monitoring can still be needed.
Do you still need liver cancer screening after hepatitis C cure?
If you have cirrhosis, yes. Current AASLD and IDSA guidance recommends continued hepatocellular carcinoma surveillance after cure because the cancer risk falls but does not disappear.
How often is liver cancer surveillance done after hepatitis C cure?
For people with cirrhosis, current guidance recommends liver cancer surveillance every 6 months, usually with ultrasound, with or without alpha fetoprotein testing according to the clinical plan.
What is hepatitis C cryoglobulinemia?
Cryoglobulinemia occurs when abnormal immune proteins form complexes that can inflame blood vessels. HCV related cryoglobulinemic vasculitis can cause purple skin spots, joint pain, fatigue, nerve problems, and kidney disease.
Can hepatitis C cause kidney disease?
Yes. HCV is linked with chronic kidney disease and immune complex kidney disease, especially membranoproliferative glomerulonephritis related to cryoglobulinemia.
Can hepatitis C cause nerve damage?
HCV related cryoglobulinemia can cause peripheral neuropathy. Symptoms may include burning, tingling, numbness, or weakness. Many other conditions can also cause these symptoms.
Can hepatitis C cause lymphoma?
Chronic HCV is associated with certain B cell non Hodgkin lymphomas. Some HCV associated lymphoproliferative disorders improve after successful antiviral treatment.
Can hepatitis C cause diabetes?
Chronic HCV is associated with insulin resistance and type 2 diabetes, but diabetes has many causes and risk factors. The relationship is more complex than saying HCV directly causes every case.
Can hepatitis C come back after cure?
A true sustained virologic response is considered a cure, but it does not create immunity. A person can become infected again after a new exposure.
Will my hepatitis C antibody test become negative after cure?
Usually not. HCV antibodies can remain positive after cure. An HCV RNA test is used to determine whether active infection or reinfection is present.
Is ascites an early hepatitis C complication?
Usually no. Ascites is much more commonly a sign of advanced cirrhosis and portal hypertension than an early complication of uncomplicated acute hepatitis C.
When should hepatitis C complications be treated as an emergency?
Seek urgent medical help for vomiting blood, black stool, new confusion, fainting, severe jaundice, rapidly increasing abdominal swelling, unusual bleeding, severe weakness, or rapidly worsening symptoms.

Health & wellness writer with 30+ years of experience in nutrition, fitness, and healthy aging. Founder of NextFitLife.com — evidence-based health guidance.

